“I thought it was just an ulcer.”
We hear some version of that sentence a lot. The sore on the tongue that showed up after a bad tooth. The hoarse voice blamed the air conditioning. A little lump under the jaw that didn’t hurt, so why bother.
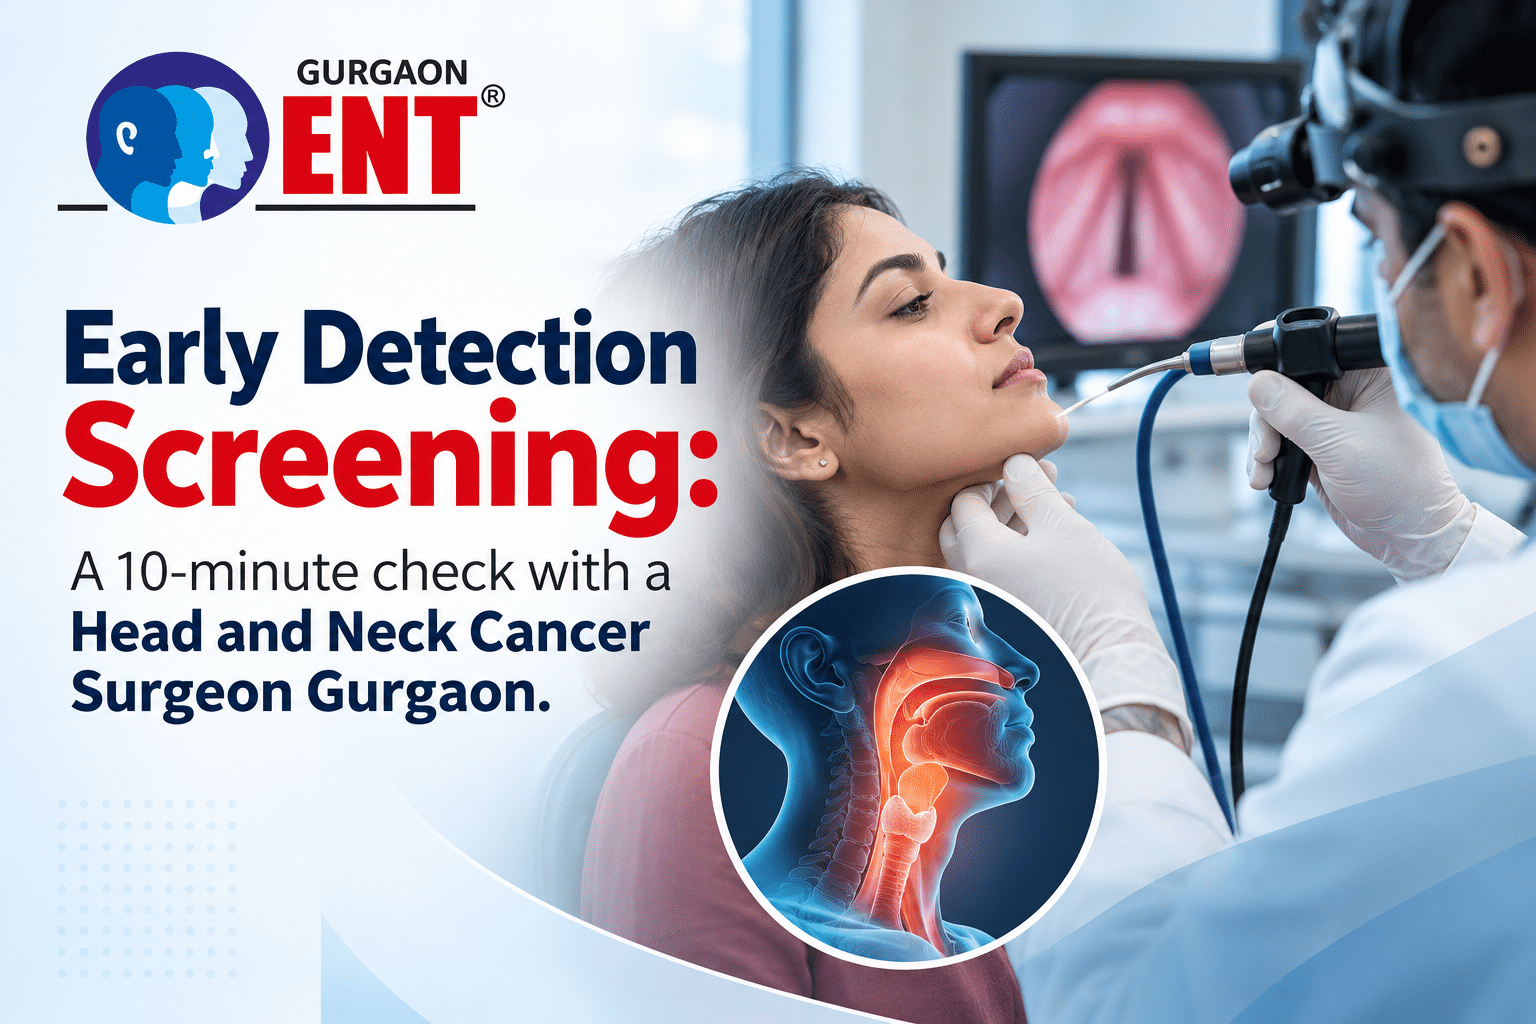
And most of the time, they’re right. Ulcers heal. Glands swell with a cold and go back down. The trouble is that in its first few weeks an early cancer looks exactly like all of that, and the one thing that tends to give it away is that it doesn’t go. So we give patients a rough rule: about three weeks. An ulcer still there after two to three weeks. A throat or voice problem that has outlasted its cold. A neck lump that hasn’t shrunk in two weeks. It’s less science than a line drawn in pencil, but it gets people through the door. A ten-minute check with a Head and Neck Cancer Surgeon Gurgaon patients can see directly will tell you which side of that line you’re on. Below we go through what happens in the check, what the research backs up, and where it runs out.
Why the wait happens
Head and neck cancers are usually found late. A review co-written by specialists from Tata Memorial Hospital and the International Agency for Research on Cancer blames delay by patients and delay inside the health system, and points out that five-year survival has stayed near 50% for decades, except at specialised centres.
The patient’s share is easy to picture. The system’s share is quieter. Take a stubborn sore throat: first course of antibiotics, no change. Second course, a little better, then back. Somewhere around week eight, someone finally looks properly. Nobody in that chain was careless, because these symptoms really do overlap with common infections. Still, every loop costs weeks. A specialist changes the question being asked. Instead of “what’s the most likely harmless cause?”, it becomes “what would make this suspicious?”
One side or both?
That’s the question we lean on most, along with how long and whether it’s changing. Infections and allergies usually hit both sides of the nose, throat and ears. So a nostril blocked on one side only, an earache in one ear while the ear looks normal, or a single tonsil bigger than the other gets more of our attention than a symmetrical complaint. The Cleveland Clinic lists persistent earache with a normal-looking ear among the symptoms, since throat pain can show up in the ear.
| What you notice | Usual harmless cause | Get it examined if |
| Mouth ulcer | Sharp tooth edge, cheek bite, acidity | Not healed in 2 to 3 weeks |
| Hoarse voice | Cold, shouting, acid reflux | Lasting a few weeks with no cold |
| Sore throat | Viral infection | Still there after the infection should be gone |
| Ear pain | Ear infection | Ear looks fine, pain continues, often one side |
| Neck lump | Gland swollen by infection | Present beyond 2 weeks, or hard and painless |
| White or red patch in mouth | Fungal infection, friction | Doesn’t clear with treatment |
| Blocked nose, one side | Allergy, deviated septum | Comes with bleeding, numbness or swelling |
Neck lumps deserve a separate word. Moffitt Cancer Center says a gland swollen by infection is usually soft, tender and slides a bit under the skin, while a cancerous node is more likely to be hard, painless and stuck in place. It also notes that HPV-related throat cancer often skips the sore throat stage, and a painless lump can be the first and only sign. Which is why “it doesn’t hurt” makes a poor reason to wait.
The numbers, with their limits
We run a clinic, so we gain when you walk in. Fair enough to lay out the evidence as it stands, including the parts that don’t flatter us.
India carries a large share of this disease. An analysis of 37 population-based cancer registries found that head and neck cancers make up about 26% of cancers in men and 8% in women, with a lifetime risk near 1 in 33 for men and 1 in 107 for women. Northern registries reported 28.5 cases per 100,000 men, second only to the northeast at 31.7.
Tobacco is behind most of it. In the national survey GATS-2, 28.6% of adults used tobacco and 21.4% used smokeless forms. A paper on smokeless tobacco in India connects those products to precancerous changes such as leukoplakia, erythroplakia and oral submucous fibrosis. But tobacco is no longer the full story. Oncologists quoted by The Week in April 2026 described more patients with no tobacco history, where HPV, oral hygiene and family history were involved.
Stage matters enormously. Using US data (SEER, patients diagnosed 2015 to 2021), the American Cancer Society reports five-year survival for tongue cancer of 88% when localized, 70% when it has reached nearby nodes, and 39% when distant. For the floor of the mouth the same three figures are 72%, 43% and 22%. Those are American numbers and Indian patients face different access and case mix, so take them as a sense of direction. The Indian data is grimmer. A cohort of 14,059 oral cancer patients from 10 registries, diagnosed between 2012 and 2015, showed 37.2% overall five-year survival, and distant spread carried four times the risk of death. The two datasets can’t be compared head to head, but they point the same way.
Now, screening itself. The best Indian evidence is the Kerala trial in The Lancet. Trained health workers inspected mouths in seven clusters over three rounds, three years apart, with six clusters as controls. For the population as a whole, the fall in oral cancer deaths wasn’t statistically clear. Among tobacco and alcohol users it was: 70 deaths in the screened group against 85 in controls. One detail has stayed with us. Only 63% of people who screened positive went for the follow-up examination.
There’s a dissenting view too. In 2013 the US Preventive Services Task Force called the evidence insufficient to recommend for or against screening symptom-free adults in primary care. That statement leaves out dentists and ENT surgeons, and it was written for a country where oral cancer is far rarer than it is here. Putting it all together, we think routinely examining low-risk people has unproven benefit, while examining high-risk people and moving quickly on symptoms that persist stands on firmer ground.
Ten minutes, in order
Ten minutes is the core examination. If we need to look further or talk through findings, the visit runs longer.
We begin by talking. How long you’ve had the symptom, whether it’s changed, whether you smoke or chew (cigarettes, bidis, khaini, gutka, tobacco paan), how much you drink, whether anyone in the family has had a head or neck cancer, whether you’ve lost weight without trying.
Then we look. In a visit with a Head and Neck Cancer Surgeon Gurgaon residents often approach for a sore that won’t heal, that means the lips, inner cheeks, gums, the sides and underside of the tongue, the floor of the mouth, the palate and the back of the throat. The tongue’s sides and underside and the floor of the mouth get extra time, because lesions there are easy to skim past. We also check how wide you can open your mouth, since slowly increasing stiffness can point to oral submucous fibrosis.
Next, the neck, by hand: lymph nodes on both sides, the thyroid, the salivary glands, the area under the jaw. We note the size and firmness of anything we find, and whether it moves freely or feels anchored to what’s beneath it.
If the problem involves the nose, throat or voice, a thin flexible endoscope lets us see the nasal passages, throat and voice box directly. It matters more than it sounds, because a torch and a mirror only reach so far. The hypopharynx, for instance, sits out of view in an ordinary mouth examination.
What it won’t tell you
It can’t diagnose cancer. Only a biopsy does that, where a small piece of tissue goes under a microscope. And a clear examination today says nothing guaranteed about next year, since a small lesion deep in the throat can slip past any single visit.
What the ten minutes can do is put you in one of three places: biopsy or scan now, recheck in a couple of weeks, or fine for the moment. That last result carries a small bonus. Your notes from today become a baseline, so if a symptom returns next year, there’s a record of how your mouth and neck looked before.
Who should come (and how often)
The strongest case is for people who use tobacco in any form, smokeless included, and for regular drinkers, especially those who also chew or smoke. Add anyone with a known HPV infection, a family history of head and neck cancer, or dentures that have started fitting badly, because jaw swelling can be the reason.
On frequency, the Kerala trial screened every three years. In our practice we suggest yearly for high-risk patients. That’s clinical judgement, not a trial result, and you should know which is which. And if you have a symptom that has lasted about three weeks, don’t hold out for the annual slot.
Age doesn’t excuse anyone. A young cricketer on our website came to Dr. Gera with swelling and pain near his eye after practice. Examination found a mass in the right nasal cavity. He had surgery and went home within 24 hours.
Why a surgeon, and not just any doctor
Dentists and family doctors often catch the first sign, and their referral counts for a great deal. But when a symptom keeps going and the answer is “let’s see how it looks next month”, you’re back in the delay from earlier. A Head and Neck Cancer Surgeon Gurgaon patients can consult directly can examine, pass a scope, plan a biopsy and operate if it comes to that, so steps that normally mean several appointments can happen in one conversation.
Dr. Ravinder Gera has spent more than 20 years in ENT surgery, covering head and neck cancer operations, cochlear implants, microscopic ear surgery, and sinus and thyroid work. Gurgaon ENT Clinic has diagnostic facilities on site. And since Dr. Gera is associated with Max Hospital, anyone needing hospital-based treatment doesn’t have to start over somewhere new.
When something looks off
Usually a biopsy comes first. Depending on the site, an ultrasound, CT or MRI may follow, to map how far a lesion extends and whether nodes are involved. If cancer is confirmed, the plan depends on the site, the stage and your general health, and can include surgery, radiation, medicines, or a mix. We walk patients through what each option means for speech, swallowing and appearance, since those are the questions that come up most. A second opinion is a perfectly reasonable request, and we’ll help arrange it.
Bring these with you
A bit of preparation makes any visit more useful, whichever Head and Neck Cancer Surgeon Gurgaon you pick. Write down the date you first noticed the problem. If it’s visible, take a dated photo on your phone. Pack old reports, the names of any antibiotics you’ve been given for it, and a list of your regular medicines. And be straight about your habits, because the advice depends on them.
On prevention, the Cleveland Clinic page above names three steps: avoid tobacco, limit alcohol, and ask your doctor about HPV vaccination. If you want help quitting tobacco, say so during the visit. It comes up often and nobody blinks.
Questions people ask
Does the examination hurt?
Not really. Looking in the mouth and feeling the neck are painless. If we use the endoscope, you may feel some pressure in the nose or a brief urge to gag.
If my result is normal, do I need to come back?
Depends on your habits. Tobacco or alcohol users should come yearly. With no risk factors, come back when something new turns up or a symptom lingers.
Can I be examined with no symptoms at all?
Yes, and for high-risk people that’s the whole idea. Early changes inside the mouth are often painless, so waiting for pain means waiting too long.
How long should I wait before getting a mouth ulcer looked at?
Two to three weeks. If it hasn’t healed by then, get it examined. Another tube of gel won’t answer the question.
Is every neck lump cancer?
No, far from it. Most come from infections or benign causes. But one that’s still there after two weeks, or feels hard and painless, needs looking at.
Will I need a biopsy or scan on the first visit?
Usually not. The first visit is mostly examination. Tests follow only if something looks unusual or unclear.
Can non-smokers get head and neck cancer?
They can. HPV, alcohol, mouth hygiene, family history and other factors play a part, and doctors are reporting more cases in people with no tobacco history.
Doesn’t my dentist already check this?
Partly. A dentist looks closely at teeth, gums and the mouth, and may be first to notice a change. A head and neck examination also covers the throat, voice box, nose and neck.
Last word
Most people we examine go home with a normal result or a harmless explanation, and that’s a perfectly good outcome. The point of the check is to shrink the gap between noticing something and having it properly looked at, because that gap is where outcomes get decided. If you use tobacco or alcohol, or a sore, a hoarse voice or a lump has crossed the three-week mark, book with a Head and Neck Cancer Surgeon Gurgaon patients can consult directly, and leave with a documented answer instead of another few weeks of wondering.
Book your screening at Gurgaon ENT Clinic. Call or message the clinic through gurgaonentclinic.com to arrange a consultation with Dr. Ravinder Gera.
Disclaimer: This article is for general information and doesn’t replace a medical examination. Survival figures are population averages and can’t predict any one person’s outcome. Please see a qualified doctor about your own symptoms.
Recent Post
-
Early Detection Screening: A 10-minute check with a Head and Neck Cancer Surgeon Gurgaon.
September 29, 2026
-
Acoustic Neuroma Monitoring: When to Watch and When to Operate with a Skull Base Surgeon in Gurgaon
September 24, 2026
-
The “Wait-and-Watch” Protocol: When a Thyroid Surgeon in Gurgaon recommends active surveillance.
September 16, 2026