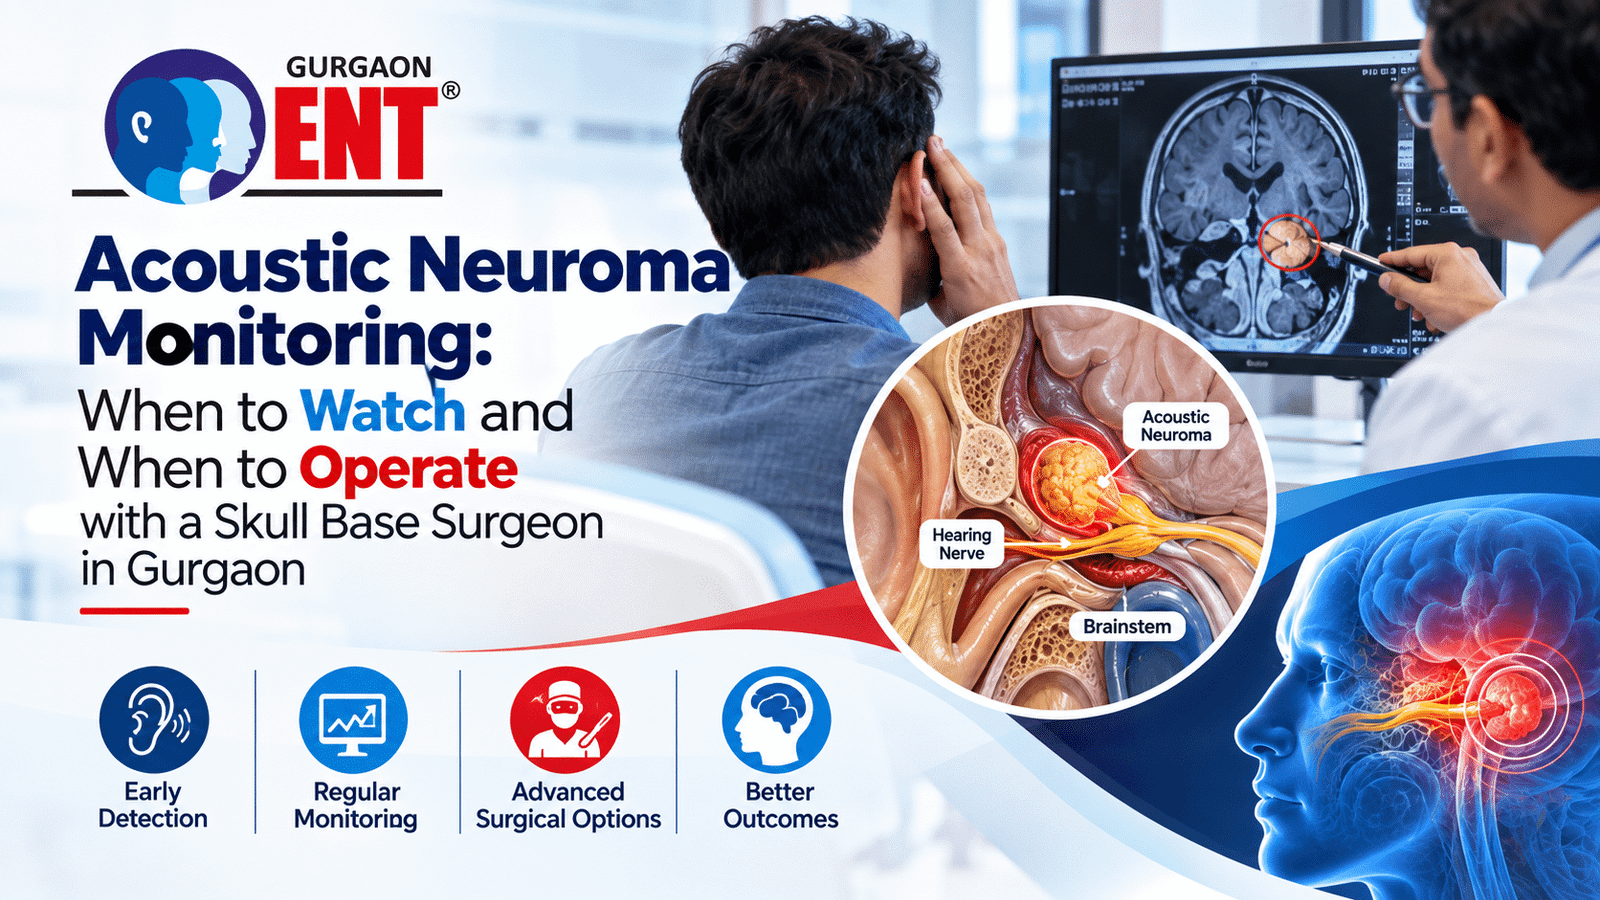
Two patients, same week, same clinic. One has an 8mm tumour confined entirely to the internal auditory canal, stable across two scans a year apart. The other has a 21mm tumour that’s grown 4mm since the last MRI and is now leaning against the brainstem. Both carry the same diagnosis on paper: acoustic neuroma. One goes home with a scan appointment for next year. The other is scheduled for surgery within a month. Same words, two completely different plans — and that gap is really the whole story of this condition. A Skull Base Surgeon in Gurgaon spends more time working out which of these two patients you resemble than treating the diagnosis itself as an instruction.
The Tumour Itself: What “Benign” Does and Doesn’t Mean
Doctors termed it as a vestibular schwannoma more than acoustic neuroma, the technically correct term or name. The acoustic neuroma developed from Schwann cells which are wrapped around the vestibular nerve, it is the same nerve which carries the balance signals from the inner ears to the brain. It is assuring that it is benign, which will not be metastasized or can be sen in your lungs years later.
What makes it complicated is location, not biology. The nerve runs through a narrow bony canal before opening into a small space near the brainstem, and there simply isn’t much room to spare down there. A 2cm benign lump in your forearm would be a non-event. A 2cm benign lump pressing on the seventh cranial nerve is a different conversation entirely.
Why These Tumours Show Up
There is no proper identifiable cause in 90 to 95% cases, they are sporadic, no clear triggering cause, no family history of the known issue. The remaining percentage of about 5%, is associated with a condition called neurofibromatosis type-2. It basically produces tumors in both sides, but not on one, and it appears at an early age, even in 20s and 30s.
Prior radiation exposure to the head or neck, typically from earlier cancer treatment, is the one environmental risk factor with reasonably solid research behind it.
Mobile phone use and long-term loud noise exposure come up constantly in patient forums as suspected causes. Neither has held up under actual study. We mention this not to lecture anyone but because patients often arrive convinced they caused this somehow, and that guilt doesn’t help the decision ahead of them.
What Actually Gets Someone Diagnosed
It’s rarely dramatic. The typical story is gradual hearing loss in one ear — missing words on phone calls, asking people to repeat themselves on one particular side, sound feeling “muffled” rather than absent. Tinnitus on the same side often tags along, and a subtle unsteadiness that people usually blame on tiredness or an old ear infection before anyone thinks to scan it. Facial numbness or tingling tends to arrive later, once a tumour has grown large enough to press against the nerve running alongside it.
An audiogram is the first real clue — specifically a pattern of asymmetric, high-frequency hearing loss with reduced word recognition on one side, sometimes paired with an absent acoustic reflex. That combination is what usually triggers the next step: an MRI with gadolinium contrast, not a CT scan, since CT can miss smaller tumours in this canal entirely.
Monitoring: The Schedule, the Grading, and the Catch Nobody Mentions
Once confirmed, the tumour gets classified using the Koos system — Grade I sits fully inside the bony canal, Grade II extends slightly beyond it without touching the brainstem, Grade III makes contact without compressing it, and Grade IV is actively pushing the brainstem out of position. This grade, paired with millimetre size, becomes the reference point for every future conversation.
A commonly followed monitoring schedule: a repeat MRI at six months, then yearly for about five years, then every two years, tapering eventually to once every five years for life if the tumour has stayed quiet throughout. The early years get watched more closely because growth behaviour in that window tends to predict what happens later — though “tends to” is doing real work in that sentence, because these tumours don’t grow on a predictable curve.
Here’s the part that doesn’t make it into most patient handouts. A single scan showing a 1 or 2mm change from the last one can just be measurement variability — a different radiologist, a slightly different slice angle, a scanner with marginally different calibration. That’s one reason a solitary reading rarely changes a treatment plan on its own. What actually shifts the conversation is a consistent trend across two or more follow-ups, or a jump large enough that measurement noise can’t reasonably explain it. Some centres have also started tracking tumour volume rather than relying only on the largest linear diameter, since volume tends to catch growth earlier — it’s a reasonable question to ask your surgeon which method they’re using when they walk you through your own scans.
Observation, Radiosurgery, or Surgery — Side by Side
| Approach | Typically fits | What it actually involves |
| Observation (watch and scan) | Tumours under roughly 15mm, minimal symptoms, intact hearing, older or medically frail patients | Scheduled MRIs on a fixed calendar; no active treatment unless the trend changes |
| Stereotactic radiosurgery | Small to medium tumours, patients wanting to avoid open surgery, or poor surgical candidates | Focused radiation (Gamma Knife or CyberKnife) aimed at halting growth — it doesn’t remove the tumour |
| Microsurgery | Larger or clearly growing tumours, brainstem contact, younger patients wanting the tumour out | Removal via translabyrinthine, retrosigmoid, or middle fossa approach, chosen by hearing status and tumour position |
When Watching Remains the Right Call
Observation tends to hold up when a tumour stays under roughly 15mm and clear of the brainstem, and when meaningful hearing is still present in that ear — surgery and radiation both carry some risk to hearing that plain monitoring doesn’t. Age cuts in the expected direction here: for a patient in their late 60s or 70s, or someone managing cardiac or other conditions that raise surgical risk, a small tumour sitting still for years usually isn’t worth disturbing. Some patients stay on this path indefinitely and never need anything beyond the scans.
One practical point that gets skipped in most articles on this topic: if hearing has already dropped noticeably on the affected side while you’re still in observation, a CROS hearing aid — a device that picks up sound from the weaker ear and routes it to the better one — can make daily conversation considerably easier during the monitoring years, without affecting the treatment decision itself. It’s a small thing, but it’s the kind of practical detail that matters more to a patient’s actual week than the millimetre count does.
When the Scans Change the Conversation
The recommendation moves toward treatment once growth crosses a threshold that’s hard to explain away as measurement noise — generally more than 2mm a year sustained across scans — or once the tumour approaches a size, often cited around 20 to 25mm, where brainstem compression becomes a realistic possibility rather than a distant one. New facial numbness, a further drop in hearing, or balance problems that are now interfering with actual daily activity all push in the same direction.
Age plays out differently on this side of the decision. In a younger, otherwise healthy patient with a tumour that’s clearly on the move, earlier surgery tends to produce better odds for hearing and facial nerve preservation than waiting until the tumour has grown substantially larger. That’s a real tension in this field: operate too early and you may be treating something that would have sat quietly for a decade; wait too long and the window for a cleaner outcome narrows. The growth pattern across scans, not the size at the first reading, is what should be doing the deciding.
What Actually Happens in the Operating Room
Three main surgical routes exist, and which one gets used depends on hearing status and where the tumour sits. Going in through the ear canal itself is generally reserved for patients who’ve already lost useful hearing on that side, since the approach sacrifices what remains. Going in from behind the ear is the route most often chosen when the surgical team is specifically trying to preserve hearing. A smaller approach through the roof of the ear canal suits certain tumours confined to the canal itself.
Throughout, the facial nerve is monitored continuously with electrical stimulation — the surgical team gets real-time feedback if instruments are getting close to it, and this single practice has shifted facial nerve preservation rates considerably compared with surgical outcomes from several decades ago. Hospital stays and initial recovery typically run from a few days to a couple of weeks; some dizziness and fatigue afterward is normal and usually settles as the brain adjusts to altered signals from that ear.
Worth saying plainly, because it doesn’t always get said plainly: hearing that’s already been lost in the affected ear generally doesn’t return, whatever treatment path is chosen. That’s precisely why the timing conversation matters as much as it does — “let’s keep watching this” is a real medical strategy, not a way of avoiding a harder conversation.
The Data Point Most Articles Skip
A 2015 quality-of-life study in the Journal of Neurosurgery, following patients across microsurgery, radiosurgery, and observation groups, found something that surprises most people: overall physical and emotional health tracked more closely with how patients felt afterward than which treatment path they’d taken. Put differently, the months spent agonizing over the decision itself may weigh on a patient nearly as much as the outcome does. That’s a reasonable argument for a second opinion or a longer conversation with your surgeon rather than more solo research at 1am — it tends to settle the decision faster than another article will.
A First Visit, Concretely
A typical first consultation for a newly diagnosed patient starts with a hearing test to establish where things stand today — that becomes the baseline everything downstream gets measured against. Next comes a walk-through of the MRI itself: Koos grade, size, and position explained in terms that mean something rather than numbers read off a report. From there, the conversation turns to what monitoring would specifically involve for that tumour versus what surgery would involve, hearing and facial nerve risks included, without smoothing over the harder parts. If surgery is the right call, the approach gets chosen based on that patient’s tumour and remaining hearing — not applied as a default because it’s the one used most often.
Frequently Asked Questions
Is this a form of brain cancer?
No — it’s benign and doesn’t spread to other organs. The risk here comes entirely from location and, if untreated, size, not from malignancy.
How often will scans actually happen if I choose monitoring?
A typical schedule runs a repeat MRI at six months, annually for around five years, then every two years, tapering to once every five years if the tumour has stayed stable throughout.
If one scan shows growth, does that mean surgery is next?
Not usually on its own. A single reading can reflect measurement variation rather than real change. It’s a consistent trend across two or more scans, or a jump too large to be explained by measurement error, that typically shifts the plan.
Does waiting longer make surgery riskier if it’s eventually needed?
Generally yes, to a degree — tumours that have grown larger before surgery tend to carry lower odds of hearing preservation and somewhat higher risk to facial nerve function, which is part of why sustained growth gets taken seriously even without new symptoms.
Is radiosurgery a substitute for surgery?
Not exactly — the goal differs. Radiosurgery aims to stop or slow growth rather than remove the tumour, which makes it a better fit for smaller tumours where controlling further growth, not physical removal, is the priority.
Should I get a second opinion before deciding?
There’s rarely a reason not to. This diagnosis isn’t usually an emergency, and the quality-of-life research above suggests that feeling settled in the decision matters almost as much as which path you choose.
Where This Leaves You
An acoustic neuroma diagnosis is a starting point, not an instruction. What comes next depends on tumour size and trend, hearing status, age, and how the numbers on two or three scans compare to each other rather than what any single report says in isolation. Some patients spend years on scheduled monitoring and never need more than that. Others reach a point where the scans make the next step clear on their own. Either way, this is a decision worth working through with a Skull Base Surgeon in Gurgaon who can sit with your specific scans rather than general averages — and if you’ve been recently diagnosed and aren’t sure which category applies to you, that’s the conversation worth having next.
Recent Post
-
Acoustic Neuroma Monitoring: When to Watch and When to Operate with a Skull Base Surgeon in Gurgaon
September 24, 2026
-
The “Wait-and-Watch” Protocol: When a Thyroid Surgeon in Gurgaon recommends active surveillance.
September 16, 2026
-
Total Middle Ear Restoration: Beyond the Drum, What a Tympanoplasty Surgeon in Gurgaon Can Rebuild
September 9, 2026